
The Next Battle Over Affordable Healthcare May Be About Specialty Drugs
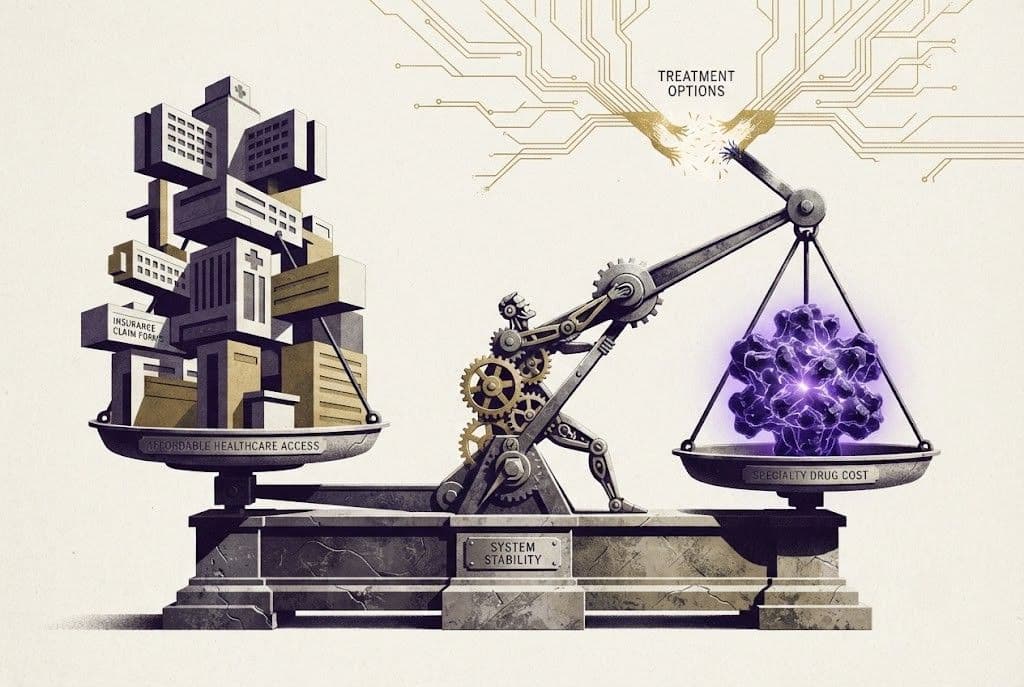
For years, the debate over affordable medicines in America has focused on the price of individual prescriptions. That approach is becoming less useful as the pharmaceutical market changes.
Generic competition has made many established medicines inexpensive, while newer specialty treatments are taking a growing share of spending. These therapies can offer important advances for cancer, autoimmune diseases, rare disorders and other complex conditions, but they can also introduce large costs into health plans and healthcare systems.
The result is a more complicated affordability problem: lower prices in parts of the pharmaceutical market do not necessarily translate into lower overall drug spending.
The shift matters particularly for employers and private insurers, which finance much of American healthcare. Employer-sponsored insurance covered roughly 154 million Americans under 65 in 2025, according to KFF. At the same time, the average annual premium for family coverage reached nearly $27,000.
A market increasingly divided between old and new
The economics of pharmaceuticals have always depended heavily on competition. Once a conventional drug loses patent protection, generic manufacturers can enter the market and push prices down. That mechanism remains powerful.
IQVIA estimates that 90% of prescriptions dispensed in the U.S. in 2024 were generic. In many major therapeutic categories, generic utilization was above 90%, and in some it approached 99%.
But prescription volume tells only part of the story.
Specialty medicines—including biologics and treatments requiring complex administration or management—represent a much smaller number of prescriptions but a disproportionately large share of spending. IQVIA estimated that specialty medicines accounted for $262 billion, or 53%, of U.S. branded medicine net sales in 2024. Specialty medicine spending had increased by more than $100 billion since 2020.
The Federal Trade Commission has similarly documented the rapid growth of specialty-drug spending, estimating that it increased from $113 billion in 2016 to $237 billion in 2023.
This creates an unusual economic structure. Millions of inexpensive prescriptions can coexist with a relatively small number of treatments that have an outsized effect on the financial performance of a health plan.
Why specialty drugs are different
Specialty medicines are not simply expensive versions of ordinary pills.
Many are biologic therapies, injectable medicines or treatments for conditions where relatively few patients are eligible. Their development can involve significant research costs and highly targeted clinical trials. Some require refrigeration, specialized distribution, infusion facilities or ongoing clinical monitoring.
That complexity affects the entire payment chain.
A hospital may purchase and administer a drug. An insurer or employer-sponsored health plan may ultimately finance much of the treatment. A pharmacy benefit manager can influence which medicines are covered and under what conditions. Manufacturers negotiate rebates and discounts, while patients can face deductibles, coinsurance or other forms of cost sharing.
Consequently, the price printed on a drug's list-price sheet is not necessarily the amount ultimately paid by every participant.
That distinction is increasingly important. IQVIA estimated that U.S. manufacturers provided roughly $536 billion in discounts in 2024, illustrating the substantial gap between list prices and net market economics.
For employers, however, the relevant question is ultimately simpler: how much does the health plan spend, and how much does that spending affect premiums, wages and benefits?
Employers are becoming more deliberate
The pressure is already visible in employer health plans.
KFF's 2025 survey found that 36% of large firms said prescription-drug prices contributed “a great deal” to higher health-plan premiums, while another 35% said they contributed “somewhat.” New prescription drugs were also identified as a significant contributor by many employers.
Employers are therefore experimenting with increasingly sophisticated benefit structures. These include multiple prescription tiers, specialty-drug tiers, utilization management and specialist networks.
Among covered workers at large firms whose plans included specialty-drug coverage, 63% were enrolled in plans with at least one separate specialty-drug cost-sharing tier in 2025. In those plans, coinsurance was more common than copayments.
The economic trade-off is straightforward but difficult. Restricting expensive treatments can reduce spending, but overly restrictive access can prevent patients from receiving therapies that may improve health or reduce other medical costs.
That makes drug management less a procurement exercise than a question of allocating scarce healthcare resources.
The specialty-drug problem is broader than cancer
Cancer treatment illustrates the issue particularly clearly because oncology increasingly includes targeted therapies, immunotherapies and other complex medicines. But the underlying economics extend into immunology, rare diseases, neurology, metabolic conditions and other areas.
The growth of GLP-1 medicines demonstrates how quickly a new category can alter an employer's calculations. KFF found that 43% of firms with at least 5,000 workers covered GLP-1 drugs for weight loss in 2025, up from 28% a year earlier. Among those firms, 66% said the drugs had a significant impact on prescription-drug spending.
This does not mean employers will necessarily reduce coverage. Some treatments may generate value through improved health, fewer complications or greater productivity. But employers increasingly have to evaluate those potential benefits alongside immediate pharmaceutical costs.
What could change the equation
Competition remains one of the strongest forces capable of moderating specialty-drug costs.
Patent expirations can open markets to generic and biosimilar competition. IQVIA estimates that patent losses could affect about $91 billion in branded revenue over the next five years, with major specialty categories including immunology and oncology expected to see additional biosimilar or generic entrants.
Policy is another variable. Medicare's recent changes to prescription-drug coverage have demonstrated how altering patient cost exposure can change medicine utilization. These policies apply directly to Medicare rather than employer plans, but they illustrate the broader relationship between insurance design, patient demand and pharmaceutical spending.
For private employers, the outcome will depend on the balance between new therapies, competitive pressure, negotiated discounts, utilization and the health benefits those treatments deliver.
The broader lesson is that America's drug-cost problem cannot be measured simply by asking whether prescription prices are rising or falling. The market is becoming increasingly divided between a vast low-cost generic base and a smaller, more financially consequential group of specialty therapies.
For employers and insurers, that changes the question from “How much does medicine cost?” to “Which medicines create enough value to justify the resources they consume?”
That is a harder question, but it is likely to become central to the next phase of healthcare affordability.